
TL;DR: Key Takeaways About Types of IBS
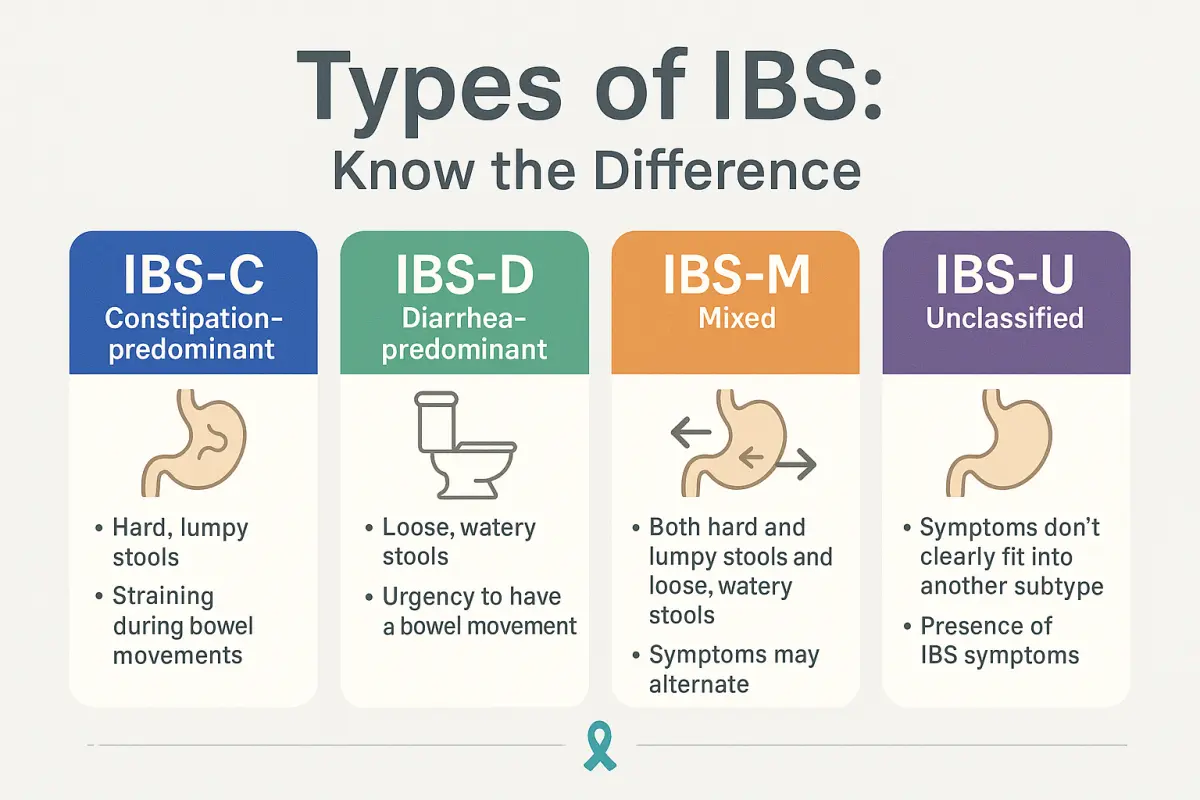
- Four main types of IBS: IBS-C (constipation), IBS-D (diarrhea), IBS-M (mixed) and IBS-U (unclassified).
- How your type is decided: by the form of your stools on the days your bowels are abnormal, using the Bristol Stool Chart and the Rome IV criteria — not by how often you go.
- Symptoms every type shares: belly pain linked to bowel movements, bloating, gas, mucus and a feeling of not emptying fully.
- Why your type matters: IBS medications, fibre and diet choices differ between IBS-C and IBS-D, and the wrong choice can make symptoms worse.
- Your type can change: many people move between subtypes over months or years, so it is worth re-checking.
- See a doctor first if you have blood in your stool, weight loss you can't explain, symptoms that started after 50, or a family history of bowel cancer or inflammatory bowel disease.
Are you struggling with unpredictable digestive symptoms but unsure which types of IBS you might have? Not knowing whether your constipation needs different treatment from diarrhea can be extremely frustrating, especially after years of trying one remedy after another.
This guide explains the different types of IBS, what each one means for your daily life, and how knowing your subtype changes the treatment that will actually help.
Understanding the Foundation: What Are the Different Types of IBS?
Irritable bowel syndrome (IBS) is a functional gut disorder — doctors now call it a disorder of gut–brain interaction. Tests and scans usually look normal, but the way the bowel moves and senses is disturbed. It affects about 1 in 10 people worldwide by older criteria and around 4% under the stricter Rome IV criteria, according to the Rome Foundation Global Study.
Types of IBS disease are not one condition with one treatment. The Rome IV criteria — the standard doctors use worldwide — sort IBS into subtypes based on stool consistency on the days symptoms are present.
When patients ask, "How many types of IBS are there?" the answer is four main subtypes. Doctors also use a label based on cause, post-infectious IBS, for IBS that starts after a gut infection. Knowing your subtype is the foundation of a treatment plan that fits.
What Causes IBS? Several Overlapping Factors, Not One
There is no single cause of irritable bowel syndrome. In most people several of these act together:
- Gut–brain miscommunication: the gut has its own network of nerves, the enteric nervous system, which talks to the brain constantly, partly through the chemical messenger serotonin. In IBS this signalling is disturbed, so normal digestion can be felt as pain.
- A more sensitive gut (visceral hypersensitivity): gas and stretching in the small and large intestine that most people would not notice cause discomfort.
- Changes in gut movement: the muscles of the large intestine move stool too fast (diarrhea) or too slowly (constipation).
- Changes in gut bacteria: the gut microbiota is often different in IBS, especially after infections or courses of antibiotics.
- A previous gut infection: see post-infectious IBS below.
- Food sensitivities: poorly absorbed carbohydrates (FODMAPs) and large fatty meals provoke symptoms in a sensitive gut.
- Stress and life history: long-term stress, anxiety and difficult life events are linked with IBS, and IBS also tends to run in families.
IBS often travels with other conditions linked to pain sensitivity, such as fibromyalgia, chronic fatigue syndrome and chronic pelvic pain, as well as indigestion. Telling your doctor about them helps them see the full picture. For more on causes, read what is IBS.
IBS Symptoms Shared by Every Type
Whatever your subtype, IBS is defined by recurrent abdominal pain on at least one day a week over the last three months, with symptoms that started at least six months ago. The pain is linked to at least two of these:
- It is related to opening your bowels (often easing, sometimes worsening, afterwards)
- It comes with a change in how often you go
- It comes with a change in how your stool looks
Most people also have some of the following:
- Bloating and a swollen belly that is often worst by evening
- Gas and loud stomach rumbling
- Mucus in the stool
- A feeling of incomplete evacuation — motion but not satisfied
- Urgency, especially after meals
- Symptoms outside the gut: tiredness, poor sleep, anxiety or low mood
For the complete list, including symptoms in women, see IBS symptoms.
An IBS flare-up usually feels like a few days of more pain, bloating and bowel changes than usual, often after a trigger such as a heavy meal, a stressful week or a disturbed routine.
The Four Primary Types of IBS and Symptoms
IBS-C: Constipation-Predominant IBS
IBS with constipation (IBS-C) is diagnosed when 25% or more of bowel movements are hard or lumpy (Bristol Stool Chart types 1–2) and less than 25% are loose or watery.
Clinical characteristics of IBS-C include:
- Fewer bowel movements than usual, often fewer than three a week
- Straining and spending a long time on the toilet
- A feeling that something is left behind after a motion
- Abdominal bloating that builds through the day
- Hard, pellet-like stools that need effort to pass
Many of our patients with IBS-C have tried isabgol, triphala or over-the-counter laxatives for years before anyone identified their type. When laxatives keep "working less", that is a signal to get properly assessed.
IBS-D: Diarrhea-Predominant IBS
IBS with diarrhea (IBS-D) shows the opposite pattern: at least 25% of stools are loose or watery (types 6–7), while less than 25% are hard or lumpy.
Defining features of IBS-D:
- A sudden, urgent need to find a toilet
- Loose stools several times a day, often in the morning or soon after eating
- Symptoms that worsen after meals (postprandial urgency)
- Mucus in the stool
- Worry about travel, long meetings or eating out
Clinical insight: IBS-D patients often develop anticipatory anxiety around meals and outings. Stress then makes the gut more sensitive through the gut–brain axis, which feeds the cycle.
IBS-M: Mixed-Type IBS
IBS with mixed bowel habits (IBS-M), sometimes called IBS-A (alternating), is diagnosed when 25% or more of stools are hard or lumpy and 25% or more are loose or watery on abnormal days.
What makes IBS-M harder to manage:
- Constipation and diarrhea alternate, sometimes within the same week
- Patterns are unpredictable, so planning meals and travel is difficult
- Treating one end too hard can tip you into the other
- It usually needs a flexible plan rather than a single medicine
IBS-U: Unclassified IBS
IBS-unclassified (IBS-U) is used when someone meets the IBS criteria but their stool pattern does not fit the other subtypes: fewer than 25% hard stools and fewer than 25% loose stools. It is common early on, and many people later settle into one of the other types.
Special Categories: IBS After Infections and IBS After Diverticulitis
Post-Infectious IBS (PI-IBS)
Post-infectious IBS starts after a bout of infectious gastroenteritis — food poisoning or traveller's diarrhea. In a systematic review of more than 21,000 people, more than 1 in 10 went on to develop IBS after infectious enteritis, about four times the usual risk. Bacterial infections such as Campylobacter, Salmonella and Shigella are common culprits. In India, where food- and water-borne gut infections are frequent, this is one of the most common stories we hear.
PI-IBS risk factors:
- Being female
- A more severe initial illness
- Antibiotic treatment during the infection
- Anxiety or depression before the infection
Post-Diverticulitis IBS
Some people develop IBS-like pain and bowel changes after an episode of diverticulitis, even once the inflammation has settled. This is less well studied than post-infectious IBS, so the right tests matter before it is labelled IBS.
How Doctors Work Out Your IBS Type (Bristol Stool Chart and Rome IV)
Your subtype comes from what your stools look like, recorded over a couple of weeks — ideally while you are not taking laxatives or anti-diarrhea medicines, which can mask the pattern.
| Bristol type | What it looks like | Group |
|---|---|---|
| Type 1 | Separate hard lumps, like nuts | Hard / lumpy |
| Type 2 | Sausage-shaped but lumpy | Hard / lumpy |
| Type 3 | Sausage-shaped with cracks on the surface | Normal range |
| Type 4 | Smooth, soft sausage or snake | Normal range |
| Type 5 | Soft blobs with clear-cut edges | Normal range |
| Type 6 | Fluffy, mushy pieces with ragged edges | Loose / watery |
| Type 7 | Watery, no solid pieces | Loose / watery |
| On days your bowels are abnormal… | Your IBS type |
|---|---|
| 25% or more are types 1–2, and under 25% are types 6–7 | IBS-C |
| 25% or more are types 6–7, and under 25% are types 1–2 | IBS-D |
| 25% or more are types 1–2 and 25% or more are types 6–7 | IBS-M |
| You meet the IBS criteria but fit none of the above | IBS-U |
A simple two-week stool diary — Bristol type, time of day, what you ate and how stressed you felt — gives your doctor far more to work with than memory alone.
What Sets Off an IBS Flare-Up
- Food: high-FODMAP foods such as wheat, onion, garlic, rajma, chole and milk, large fatty or fried meals, caffeine and alcohol. See our guide to the worst foods for IBS.
- Stress and the gut–brain axis: the gut and brain signal each other constantly, and exams, deadlines or family stress make the gut more sensitive.
- Irregular meals and sleep: skipping breakfast and then eating a heavy late dinner is a common pattern behind evening bloating.
- Gut infections and antibiotics, which disturb the gut microbiota.
- Hormonal changes: many women notice symptoms worsen around their periods.
- Some medicines: iron tablets can constipate, and metformin or magnesium can loosen stools.
Conditions That Can Look Like IBS
IBS should be diagnosed only after a doctor has taken a careful medical history, done a physical examination and considered conditions with similar symptoms. Depending on your symptoms and age, they may check for:
- Coeliac disease — a blood test for coeliac antibodies, especially with diarrhea or mixed symptoms
- Lactose intolerance — a trial without dairy, or a breath test
- Inflammatory bowel disease (Crohn's disease, ulcerative colitis) — a stool test for faecal calprotectin, and colonoscopy if needed. Read IBD vs IBS for how they differ
- Thyroid problems — an underactive thyroid can cause constipation, an overactive one diarrhea
- Gut infections and parasites such as Giardia — stool tests
- Bowel cancer — colonoscopy if you are older or have red-flag symptoms
The ACG clinical guideline for IBS recommends a positive diagnosis based on symptoms plus a limited set of these tests, rather than endless investigations.
Types of IBS Medications: Tailored Treatment Approaches
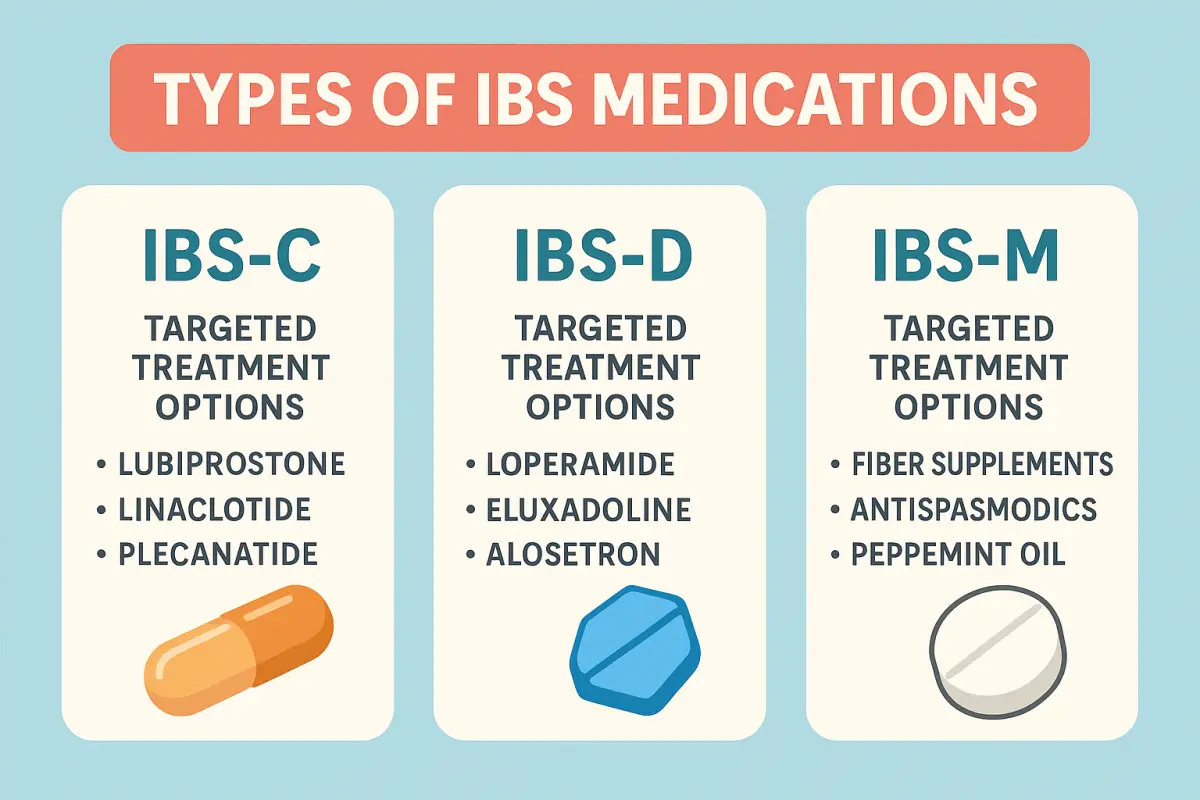
Understanding types of IBS medications means matching how a medicine works to your subtype:
IBS-C Targeted Therapies
- Linaclotide: increases fluid in the bowel and reduces pain sensitivity
- Lubiprostone: activates chloride channels to soften stool and ease movement
- Plecanatide: helps improve stool consistency
- Osmotic laxatives: polyethylene glycol for gentle, predictable relief
IBS-D Management Options
- Alosetron: for severe IBS-D in women, under specialist care
- Eluxadoline: reduces bowel contractions and urgency
- Rifaximin: a gut-selective antibiotic used for IBS-D
- Antispasmodics: such as dicyclomine for cramping
Gut–brain medicines (neuromodulators): low doses of tricyclic antidepressants such as amitriptyline are recommended in the ACG guideline for ongoing IBS pain. At these doses they calm the gut's nerve signalling rather than treat depression; SSRIs are sometimes used too.
Not all of these are sold in India; your doctor will suggest what is available and suitable for you.
IBS-M Combination Strategies
Mixed-type IBS needs a flexible plan that can respond to whichever end you are at, without overcorrecting into the opposite pattern.
At IBS Clinic, Ayurvedic treatment is matched to type in the same way: the herbal combinations we use for IBS-C, IBS-D and IBS-M are different, and each is adjusted as your pattern changes.
When to See a Doctor About IBS Symptoms
See a doctor promptly, rather than self-treating, if you have any of these red-flag symptoms:
- Weight loss you can't explain
- Blood in your stool or black, tarry stools
- A family history of inflammatory bowel disease or bowel cancer
- Symptoms that start after the age of 50
- Anaemia, or symptoms that wake you at night
Personalized Nutrition Strategies by IBS Type
A low-FODMAP diet helps across subtypes: about three in four people with IBS improve, according to Monash University, which developed it. It works best as a short elimination followed by careful reintroduction, ideally with guidance, so you don't cut out more foods than you need to.
Fibre by Type
Soluble fibre such as psyllium (isabgol) is recommended for IBS in the ACG guideline and helps most subtypes when increased slowly with enough water. Insoluble fibre such as wheat bran tends to worsen bloating and pain, especially in IBS-D.
- IBS-C: build up soluble fibre slowly and drink enough water
- IBS-D: eat smaller meals, and limit caffeine, fried food and very spicy food
- IBS-M: keep meals regular and change one thing at a time
Advanced Treatment Considerations
Gut-Directed Psychological Therapies
Because IBS is a disorder of gut–brain interaction, therapies such as cognitive behavioural therapy (CBT), relaxation techniques and gut-directed hypnotherapy are recommended in the ACG guideline for people whose symptoms persist. They help across all IBS types.
Probiotics
Evidence for probiotics is still mixed. The ACG guideline does not recommend them for overall IBS symptoms, although some people find a particular product helpful. Ask your doctor before spending on them.
Constipation with Gastrocolic Reflex Dysfunction (GCR-D)
Constipation is a common digestive complaint, but in some patients, the underlying issue is not just slow stool movement — it lies in a disordered gastrocolic reflex.
The gastrocolic reflex is the body's natural signal that prompts the bowels to contract and empty after eating. In healthy individuals, this reflex ensures timely and complete evacuation. However, in Gastrocolic Reflex Dysfunction (GCR-D), this signaling becomes weak, delayed, or paradoxical.
How GCR-D–related Constipation Differs from Simple Constipation
- Simple / Habitual Constipation
- Managed with laxatives, fiber, water intake, or fruits
- Works because stool softens and bulk + hydration help movement
- GCR-D Constipation
- The bowel does not respond properly to the gastrocolic reflex
- Laxatives, fiber, and water often backfire — worsening bloating, gas, and discomfort
- Patients feel incomplete evacuation, heaviness, or the need to strain despite lifestyle efforts
Common Symptoms of Constipation with GCR-D
- Persistent constipation unrelieved by laxatives or high-fiber diets
- Bloating and excessive gas after meals
- Abdominal discomfort or cramps, especially post-meal
- Straining with incomplete evacuation
- Anxiety around eating due to post-meal discomfort
When to Schedule Your Consultation
Consider a specialist evaluation if you experience:
- Symptoms that interfere with work, travel or social life
- No lasting response to two or more over-the-counter treatments
- A change in your usual pattern, or symptoms getting worse
- Anxiety about eating, or skipping meals to avoid symptoms
Understanding your specific types of IBS removes guesswork from treatment. If you are not sure which type you have, or what you have tried has stopped working, book a free IBS evaluation and our doctors will build a plan around your subtype, history and diet.
Frequently asked questions
What are the 4 types of IBS?+
The four types of IBS are IBS-C (constipation-predominant), IBS-D (diarrhea-predominant), IBS-M (mixed, alternating between the two) and IBS-U (unclassified, when the pattern fits none of the others). The type is based on stool form on the days your bowels are abnormal.
How do I know which type of IBS I have?+
Keep a two-week stool diary using the Bristol Stool Chart. If 25% or more of abnormal stools are hard (types 1–2) you likely have IBS-C; if 25% or more are loose (types 6–7), IBS-D; if both, IBS-M. A doctor confirms the diagnosis and rules out other conditions.
What is type 7 poop in IBS?+
Type 7 on the Bristol Stool Chart is entirely watery stool with no solid pieces. Frequent type 6–7 stools point towards IBS-D. Sudden watery diarrhea with fever, blood or severe pain is not typical IBS and needs prompt medical attention.
Is IBS-D or IBS-C worse?+
Neither is medically worse. IBS-D tends to disrupt daily life through urgency, while IBS-C causes more straining, bloating and discomfort. Severity depends on the person, and both respond well to treatment matched to the subtype.
Can your IBS type change over time?+
Yes. Many people move between subtypes, for example from IBS-C to IBS-M, over months or years. Medicines, diet changes, infections and stress can all shift the pattern, so your type should be reviewed if your symptoms change.
What triggers an IBS flare-up?+
Common triggers are high-FODMAP foods, large fatty or fried meals, caffeine and alcohol, stress, irregular meals or sleep, gut infections, antibiotics and, for many women, the days around a period. Triggers differ from person to person.
What conditions are mistaken for IBS?+
Coeliac disease, lactose intolerance, inflammatory bowel disease, thyroid problems, gut infections such as Giardia and, in older adults, bowel cancer can all cause IBS-like symptoms. Doctors use a few targeted tests to rule these out.
Can IBS be cured permanently?+
IBS has no single one-time cure, but most people can bring their symptoms under control and live normally with the right plan. Identifying your subtype and triggers, and treating the gut–brain connection, makes long-term relief far more likely.